
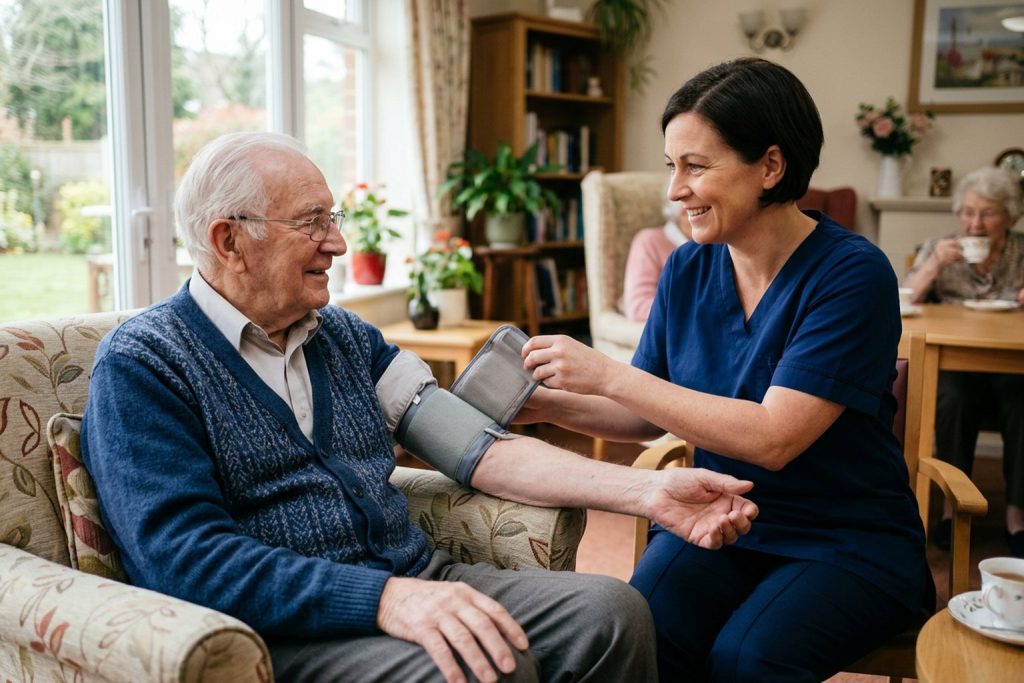
Consent in health and social care means a person’s voluntary, informed agreement to care, treatment or support, given by someone who has the capacity to make that decision. Two points are routinely misunderstood. First, a signature is not what makes consent valid: consent can be spoken or shown by action — CQC guidance gives the example of “someone rolling up their sleeve to have their blood pressure taken” — and a signed form means little if the person was pressured, poorly informed or lacked capacity. Second, a relative does not have a general legal right to consent on behalf of another adult. In England and Wales, only an attorney under a health and welfare lasting power of attorney or a court-appointed deputy can make those decisions for someone, within their authority; otherwise the person providing care decides in the person’s best interests under the Mental Capacity Act 2005, after consulting family and carers.
At a glance: Nexis CPD’s £9 Consent in Health and Social Care course covers the law and practice of consent — capacity, the Mental Capacity Act, best-interests decisions, advance decisions and when treatment may proceed without consent. It is CPD accredited and 100% online with a verifiable e-certificate, and any three courses cost £18. It is awareness training: it does not make anyone competent to carry out formal capacity assessments for complex decisions, and it does not replace your employer’s consent policy or the professional guidance of your regulator.
What is consent in health and social care?
Consent is permission, given before an action takes place, for someone to provide care, treatment, an examination or support. It applies to far more than surgery. Helping someone wash and dress, giving medication, using a hoist, taking a blood sample or photographing a wound — each needs the person’s agreement, or a lawful basis for acting without it.
For CQC-registered providers in England, this is not only good practice but a legal requirement. Regulation 11 of the Health and Social Care Act 2008 (Regulated Activities) Regulations 2014 states plainly: “Care and treatment of service users must only be provided with the consent of the relevant person.” Where a person aged 16 or over lacks capacity to consent, the provider must act in accordance with the Mental Capacity Act 2005, and where specified parts of the Mental Health Act 1983 apply, the provider must follow that Act instead.
CQC’s guidance on Regulation 11 notes that CQC can move directly to prosecution for a breach, without first serving a warning notice.
What makes consent valid?
The NHS summary of consent to treatment sets out the three conditions that practitioners, lawyers and regulators all come back to. For consent to be valid, it must be:
- Voluntary — the decision must be the person’s own, not the result of pressure from staff, friends or family.
- Informed — the person must be given the information they need: what the care or treatment involves, its benefits and risks, reasonable alternatives, and what will happen if it does not go ahead.
- Given with capacity — the person must be able to understand the information and use it to make a decision.
If any one of the three is missing, the consent is flawed — however neat the paperwork. A resident who agrees because a senior carer made clear there was no real choice has not consented voluntarily, and a patient who signed a form without being told about a significant risk has not given informed consent.
Does consent have to be in writing?
Generally, no. The NHS explains that consent can be given verbally — for example, a person saying they are happy to have an X-ray — or in writing, such as signing a consent form for surgery, and that someone can also give non-verbal consent “as long as they understand the treatment or examination about to take place”, for example by holding out an arm for a blood test.
CQC’s Regulation 11 guidance makes the same point for care services: “Consent may be implied and include non-verbal communication such as sign language or by someone rolling up their sleeve to have their blood pressure taken or offering their hand when asked if they would like help to move.”
So what is a consent form for? It is evidence that a consent conversation took place and what was discussed. That is valuable — especially for significant procedures — but the form is a record of consent, not the consent itself. Health professionals also have record-keeping duties of their own: the NMC Code, for example, requires nurses, midwives and nursing associates to “make sure that you get properly informed consent and document it before carrying out any action”. In day-to-day social care, most consent is verbal or implied, and the daily notes and care plan should show that the person’s agreement is being sought and respected.
There are specific exceptions where the law does require writing. The most important one in care settings is an advance decision to refuse life-sustaining treatment: under section 25 of the Mental Capacity Act, it only applies to such treatment if it is in writing, signed, witnessed, and includes a statement that it is to apply even if life is at risk.

What does “informed” consent actually require?
The landmark case is Montgomery v Lanarkshire Health Board [2015] UKSC 11, decided by the UK Supreme Court on 11 March 2015. It moved the focus from what doctors would usually say to what the patient needs to know.
The Supreme Court held that a doctor is “under a duty to take reasonable care to ensure that the patient is aware of any material risks involved in any recommended treatment, and of any reasonable alternative or variant treatments.” It defined materiality as whether “a reasonable person in the patient’s position would be likely to attach significance to the risk, or the doctor is or should reasonably be aware that the particular patient would be likely to attach significance to it.”
Two practical lessons follow for anyone seeking consent:
- It is a conversation, not a leaflet. Information must be tailored to what matters to this person, not a standard list.
- Alternatives count. People need to know the reasonable options, including doing nothing, not just the option being recommended.
For doctors, the GMC’s guidance Decision making and consent, in effect since 9 November 2020, applies these principles in practice.
In social care the principle is identical. CQC guidance says that information about proposed care and treatment “must be provided in a way that they can understand”, including information about risks, complications and alternatives, and that discussions “must be held in a way that meets people’s communication needs” — which may mean different formats or languages, a speech and language therapist, or an independent advocate.
Is consent a one-off?
No. CQC’s guidance is explicit: “Consent must be treated as a process that continues throughout the duration of care and treatment, recognising that it may be withheld and/or withdrawn at any time.” The NHS makes the same point about procedures: if someone changes their mind at any point before a procedure, they are entitled to withdraw their earlier consent.
In practice, this means checking in every time. A resident who agreed to a bath on Monday has not agreed to a bath every Monday for the rest of their stay. Care plans describe the agreed approach; they do not replace asking, and they do not override a refusal made today by someone with capacity.
Can a person with capacity refuse care or treatment?
Yes — and this is where good intentions most often slide into unlawful practice. The NHS states that if an adult has the capacity to make a voluntary and informed decision to consent to or refuse a particular treatment, their decision must be respected, “even if refusing treatment would result in their death, or the death of their unborn child.”
The Mental Capacity Act backs this up. Section 1 sets out five principles, and two of them bite directly on refusals:
- “A person must be assumed to have capacity unless it is established that he lacks capacity.”
- “A person is not to be treated as unable to make a decision merely because he makes an unwise decision.”
A refusal that staff disagree with is not, on its own, a reason to question capacity. Staff should make sure the person has the information they need, explore their reasons and alternatives, record the conversation, and escalate significant risks to a senior or clinical colleague. CQC’s guidance adds a balancing point: providers must not provide unsafe or inappropriate care just because someone has consented to it. Consent is necessary, but it is not a licence for poor care.
What happens when a person lacks capacity to consent?
Capacity is decision-specific and time-specific. Section 2 of the Mental Capacity Act says a person lacks capacity in relation to a matter if, at the material time, they are unable to make a decision for themselves because of an impairment of, or a disturbance in the functioning of, the mind or brain. It does not matter whether that impairment is permanent or temporary, and lack of capacity cannot be established merely by reference to a person’s age, appearance, condition or behaviour.
Section 3 sets the functional test. A person is unable to make a decision if they cannot:
- understand the information relevant to the decision;
- retain that information;
- use or weigh that information as part of the process of making the decision; or
- communicate their decision, whether by talking, using sign language or any other means.
Two details are often overlooked. A person is not unable to understand if they can understand an explanation given “in a way that is appropriate to his circumstances (using simple language, visual aids or any other means)”, and retaining information only briefly does not by itself mean they cannot decide. That is why taking all practicable steps to help a person decide matters so much in dementia and learning disability care.
Where a person does lack capacity for a particular decision, the care or treatment must be in their best interests. Section 4 requires the decision-maker to consider, so far as reasonably ascertainable, the person’s past and present wishes and feelings, their beliefs and values, and the other factors they would be likely to consider, and to take into account the views of anyone the person named to be consulted, anyone caring for them or interested in their welfare, and any attorney or deputy. The final principle in section 1 asks whether the purpose can be achieved “in a way that is less restrictive of the person’s rights and freedom of action.”
Our guide to the Mental Capacity Act goes through the five principles and the two-stage test in more detail, and our guide to DoLS explains what happens when care arrangements amount to a deprivation of liberty.
How are care staff protected when they act in someone’s best interests?
Section 5 of the Act protects people who act “in connection with the care or treatment” of someone, provided they first take reasonable steps to establish whether the person lacks capacity and reasonably believe the act is in their best interests. That is what makes helping someone who lacks capacity to wash, dress or eat lawful. It does not protect against negligence, and under section 6, restraint is only covered where it is necessary to prevent harm and proportionate to the likelihood and seriousness of that harm.
Can next of kin consent on behalf of an adult?
Not simply because they are next of kin. The term has no special legal standing for consent to an adult’s care or treatment in England and Wales. The people who can make decisions on an adult’s behalf are:
- An attorney under a lasting power of attorney (LPA) for health and welfare. Under section 11, the attorney’s authority only applies when the person lacks (or the attorney reasonably believes they lack) capacity for the decision, and it only extends to life-sustaining treatment if the LPA expressly says so.
- A deputy appointed by the Court of Protection, within the powers the court has given them.
- The Court of Protection itself, for disputed or serious cases.
Otherwise, the professional responsible decides in the person’s best interests, taking family members’ views into account. The NHS notes that if a person lacks capacity and has not appointed an LPA, clinicians “must take reasonable steps to discuss the situation with the person’s friends or relatives” before making decisions. Families are important consultees — but consulting them is different from asking them to consent.
Where there is nobody appropriate to consult, the Act adds a safeguard for certain serious decisions. Under section 37, for example, an NHS body proposing serious medical treatment for a person who lacks capacity, and who has nobody other than paid carers or professionals to consult, must instruct an Independent Mental Capacity Advocate (IMCA) to represent them before the treatment is provided, except where it is urgent.
What is an advance decision?
An advance decision is a decision made by someone aged 18 or over, while they have capacity, to refuse a specified treatment if at a later time they lack capacity to consent to it (section 24). It can be expressed in everyday language, and the person can withdraw or change it at any time while they have capacity — a withdrawal need not be in writing.
A valid and applicable advance decision has the same effect as a refusal made at the time. But section 25 sets conditions. It does not apply if the person has capacity at the time (they can simply decide), if the treatment or circumstances do not match what it specifies, or if there are reasonable grounds to believe circumstances exist that the person did not anticipate and which would have affected their decision. And, as noted above, a refusal of life-sustaining treatment only applies if it meets the formal written, signed, witnessed and “even if life is at risk” requirements. An advance decision can only refuse treatment; wider written wishes must be considered in best-interests decisions under section 4(6), but are not binding in the same way.

Can medicines be given covertly?
Only in narrow circumstances. NICE guideline SC1, Managing medicines in care homes, recommends that practitioners “should not administer medicines to a resident without their knowledge (covert administration) if the resident has capacity to make decisions about their treatment and care.” Where covert administration is being considered for an adult who lacks capacity, NICE recommends a process that includes assessing capacity, holding a best-interests meeting involving care home staff, the prescriber, a pharmacist and a family member or advocate, recording the reasons and the management plan, planning how the medicines will be given, and regularly reviewing whether covert administration is still needed.
Crushing tablets into food informally because “she won’t take them otherwise” does not follow that process. Our guide to the 6 rights of medication administration covers the wider medicines framework.
What does good consent practice look like day to day?
Most consent in care happens in small moments, dozens of times a shift. Good practice usually looks like this:
- Ask before you act — every time, even for routine care, and wait for an answer.
- Explain in a way the person can understand — plain words, pictures, their own language, hearing aids and glasses in place.
- Offer real choices rather than a single option, and respect “no” — try again later or differently rather than insisting.
- Watch for non-verbal refusal — pulling away, pushing a hand aside, turning the head from a spoon.
- Record and escalate — note consent given or refused, and raise capacity doubts about significant decisions with a senior colleague.
These habits sit at the heart of person-centred care and dignity in care.
What training in consent do care workers need?
CQC’s Regulation 11 guidance states that providers must make sure staff who obtain consent “are familiar with the principles and codes of conduct associated with the Mental Capacity Act 2005, and are able to apply those when appropriate”. The Mental Capacity Act Code of Practice is the statutory guidance that sits alongside the Act. No law prescribes a particular consent course or certificate; what matters is applying the law correctly in practice.
An online awareness course is a proportionate way to give care workers the core knowledge. It is not a substitute for supervised practice, your organisation’s policies or your regulator’s guidance, and it does not make a care worker competent to lead complex capacity assessments or best-interests decisions about serious medical treatment.
Which courses support consent in care?
Three £9 courses fit together well, each with a verifiable certificate for training records:
- Consent in Health and Social Care — capacity, the Mental Capacity Act, best interests, advance decisions and when treatment can proceed without consent.
- Mental Capacity Act — the five principles, the capacity test and best-interests decision-making in more depth.
- Dignity in Care — the everyday practice of choice, privacy and respect that good consent depends on.
Those three together cost £18 rather than £27, because any three courses trigger the pay-for-2-get-3 offer. Add them to the cart and the discount applies automatically.
Frequently asked questions
What are the three elements of valid consent?
Consent must be voluntary, informed and given by a person with capacity. Voluntary means the decision is the person’s own, free from pressure. Informed means they have been told what the care or treatment involves, its benefits and risks, reasonable alternatives and what happens if they decline. Capacity means they can understand, retain and weigh the information and communicate a decision.
Does consent in care have to be written down?
Generally no. Consent can be verbal, written or implied by actions, such as holding out an arm for a blood test. CQC guidance confirms consent may be implied, including non-verbal communication. A signed form is evidence that consent was sought, not what makes it valid. Specific exceptions exist, such as an advance decision refusing life-sustaining treatment, which must be written, signed and witnessed.
Can a family member consent for an adult who lacks capacity?
Not simply as next of kin. In England and Wales, only an attorney under a health and welfare lasting power of attorney, a deputy appointed by the Court of Protection, or the court itself can make such decisions on an adult’s behalf. Otherwise the professional responsible decides in the person’s best interests under the Mental Capacity Act 2005, taking family members’ views into account.
Can someone refuse care even if it puts them at risk?
Yes, if they have capacity for that decision. The Mental Capacity Act says a person must be assumed to have capacity and must not be treated as unable to decide merely because they make an unwise decision. Staff should make sure the person is fully informed, explore alternatives, record the discussion and escalate significant risks, but must respect a capacitous refusal.
What did the Montgomery case change about consent?
Montgomery v Lanarkshire Health Board [2015] UKSC 11 held that clinicians must take reasonable care to ensure patients are aware of any material risks of recommended treatment and of reasonable alternatives. A risk is material if a reasonable person in the patient’s position would likely attach significance to it, or the clinician should know that this particular patient would.
Is covert medication ever allowed in a care home?
Only in narrow circumstances. NICE guideline SC1 says medicines should not be given covertly to a resident who has capacity to make decisions about their treatment. For someone who lacks capacity, covert administration should follow a documented process including a capacity assessment, a best-interests meeting with the prescriber, a pharmacist and family or an advocate, a plan, and regular review.
Put consent at the centre of care
£9 per course. CPD accredited, 100% online, verifiable e-certificate. Pay for 2, get 3 — any 3 courses for £18.
This article is general information, not legal or clinical advice. It describes the law in England and Wales; Scotland and Northern Ireland have different mental capacity legislation. A Nexis CPD awareness course is CPD accredited but is not a regulated qualification; it does not qualify anyone to carry out complex capacity assessments, does not replace your employer’s consent and mental capacity policies, and does not replace the guidance of the GMC, NMC or other professional regulators. Legal references are drawn from legislation.gov.uk, CQC, NICE, NHS and UK Supreme Court sources at the time of writing.